
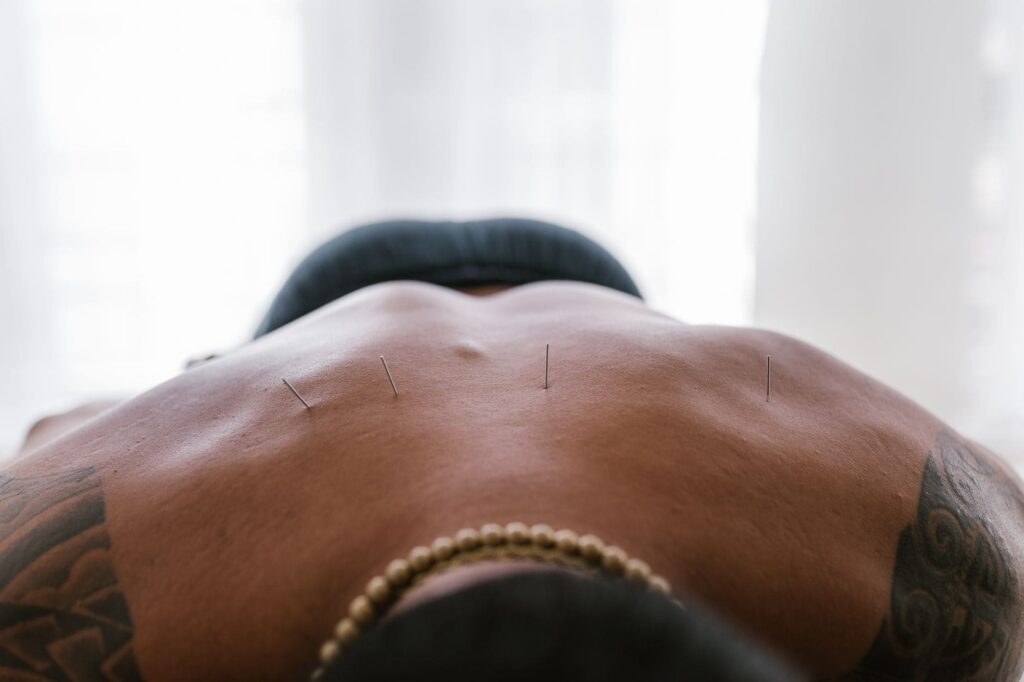
Both treatments use thin needles. Both are performed by trained clinicians. Both help pain. And yet they are entirely different practices, with different philosophies, different targets, and different evidence bases. If you have been offered one or the other and cannot tell them apart, this comparison settles it.
Key Takeaway: Acupuncture is rooted in traditional Chinese medicine and works through meridian points to influence the body’s energy and healing systems. Dry needling is a modern physiotherapy technique that targets muscle trigger points directly to release tension and reduce pain. The same needle, different maps: choose based on whether your problem is muscular (dry needling’s strength) or you want the whole-system approach (acupuncture’s territory). Many patients benefit from both.
What dry needling actually is
Dry needling targets myofascial trigger points: the taut, irritable bands inside muscles that produce local pain, referred pain, and that deep ache physiotherapists spend their days hunting. The needle goes into the trigger point itself, eliciting a local twitch response, a brief involuntary contraction, which is the mechanical event that releases the band. For patients dealing with tight muscles and localized tension, our dry needling treatments focus directly on releasing muscular trigger points to restore mobility.
Many patients also ask about acupuncture and dry needling side by side, which we cover in another post.
What dry needling treats best
- Muscle knots and trigger points: the classic “that spot that refers when you press it”
- Tension patterns: the desk neck, the runner’s calves, the lifter’s shoulders
- Deep muscle layers that hands and foam rollers cannot reach: the piriformis, the deep hip rotators
- Chronic muscle tension accompanying tendinopathy or joint problems
The name “dry” distinguishes it from injection techniques: the needle carries nothing. The treatment is the mechanical event, and the science describes it in those terms: local twitch, altered muscle fiber length, changed chemistry at the trigger point, and a nervous-system effect that reduces sensitivity.
What acupuncture actually is
Acupuncture is a complete medical system from traditional Chinese medicine, over two thousand years old, treating the whole person through points mapped along meridians. The philosophy targets qi, the body’s vital energy, and the modern research program studies its effects on pain pathways, inflammation, and central nervous system modulation. On the other hand, traditional acupuncture therapy takes a holistic approach to healing by stimulating specific points to relieve pain and balance the nervous system.
What acupuncture treats best
- Whole-body patterns: stress, sleep, headaches, digestive complaints alongside pain
- Chronic pain conditions with a central sensitivity component
- Conditions where the whole-system approach fits: fibromyalgia-style presentations, stress-tension cycles
- Patients seeking a lower-touch, deeply calming treatment style
The needles stay in place longer, often 15 to 30 minutes, and the session is quiet and restful. Many patients sleep on the table; that response is part of the design.
The side-by-side comparison
| Feature | Dry needling | Acupuncture |
|---|---|---|
| Root tradition | Modern Western medicine | Traditional Chinese medicine |
| Target | Trigger points in muscle | Meridian points, whole-body patterns |
| Needle behavior | In and out, twitch elicited | Inserted and retained 15-30 min |
| Session feel | Active, specific, intense in spots | Calm, restful, whole-body |
| Best for | Specific muscle knots and tension | Systemic patterns, chronic sensitivity |
| Typical course | 1-3 sessions per region | 4-8 sessions, weekly |
How to choose: the decision path
Question 1: Can you point at the problem?
If your pain lives in specific spots, the knot under the shoulder blade, the deep buttock ache, the forearm band, dry needling’s precision matches the problem. If your complaint is diffuse, everything is tight, everything aches, the whole system is stressed, acupuncture’s whole-body map fits better.
Question 2: What is your nervous system doing?
Stressed, sleeping badly, running on caffeine and deadlines: the calm-retained-needle format of acupuncture often produces the shift that releases everything else. Dry needling is more stimulating; the wrong week for it can leave you feeling worked rather than relieved.
Question 3: What did assessment find?
The most honest answer: the clinician finds it. Palpation that reproduces your pain in a taut band is dry needling’s target confirmed. Diffuse sensitivity without a discrete trigger point suggests the acupuncture map. Our physiotherapists and acupuncturists work in the same clinic and refer in both directions.
What each feels like, honestly
Dry needling, session by moment
- The needle insertion: a pinch, often unfelt; the needles are hair-thin
- The twitch response: a brief, deep cramp inside the muscle, 1 to 2 seconds, followed by release; this is the treatment working, and it surprises everyone the first time
- After: 24 to 48 hours of muscle soreness, the same family as a hard workout, then noticeably looser
Acupuncture, session by moment
- Insertion: barely felt, a tickle or tiny pinch
- Retention: the needles rest, sometimes with gentle warmth or stimulation; the body settles, often deeply
- De qi: a mild heaviness or warmth at points, the traditional sensation of the point activating
- After: relaxed, sometimes euphoric-tired, occasionally next-day mild fatigue as the system recalibrates
The evidence bases, honestly framed
Both fields carry research, and both carry honest limits.
- Dry needling: solid evidence for short-term pain reduction and range improvement in myofascial trigger points; best when combined with exercise, which is how we deploy it. Dry needling is often used alongside myofascial release techniques to completely break down stubborn scar tissue and improve tissue flexibility.
- Acupuncture: evidence for chronic pain conditions, headache, and osteoarthritis pain in large meta-analyses; the mechanism debate continues in the literature without slowing the clinical outcomes
- Neither replaces exercise, load management, and strength work; both accelerate the journey those tools are already on
When the two work together
The sequence we use most: dry needling releases the specific drivers, acupuncture supports the system between physiotherapy sessions, and the loading program builds what both have unlocked. Patients with chronic pain patterns often run exactly this trio.
Patients seeking acupuncture in Milton or dry needling get both under one roof, which matters when the choice between them is a clinical question rather than a menu preference.
Safety, in both hands
Both practices are safe when performed by trained, registered clinicians. The safety checklist is the same:
- Single-use, sterile needles, disposed in sharps containers
- Full screening: blood thinners, pregnancy, needle phobia, compromised immunity
- Anatomical training: the difference between a trained clinician and a weekend course is the map of what lies beneath each point
Dry needling’s common after-effects: local soreness, occasional minor bruising, the rare treatment-induced fatigue day. Acupuncture’s: similar, plus the occasional deep relaxation that makes driving home feel slower. Neither should produce sharp lasting pain; report it if it does.
The trigger point primer: what dry needling is actually treating
Understanding the target makes the treatment make sense. A trigger point is a section of muscle fiber stuck in contraction: a patch of the muscle that forgot how to release. The patch produces three problems:
- Local pain: the tender spot you can find with a fingertip
- Referred pain: patterns that project elsewhere, the classic being a shoulder-blade knot referring up behind the eye
- Weakness and stiffness: the affected muscle cannot lengthen or generate force cleanly
Trigger points form from overload, repetition, poor sleep, stress, and guarding after injury. They are the muscle’s version of a cramp that never fully cleared, and dry needling is the most direct tool that exists for releasing them.
Why hands and rollers sometimes cannot reach them
The most influential trigger points live deep: the piriformis under the glutes, the deep neck extensors under the shoulder blades, the psoas at the spine’s front. A thumb reaches centimeters; a needle reaches the layer. That depth is dry needling’s whole advantage, and the reason physiotherapists reach for it after the surface work has done what it can.
What acupuncture’s map adds that muscles miss
The meridian system treats connections that muscle anatomy does not explain, and patients experience those connections clinically: the stress-gut-headache cluster, the sleep-pain spiral, the whole-body tension that no single muscle owns. Acupuncture’s map has been navigating those patterns for centuries, and its research program continues documenting the mechanisms.
For the patient with three separate complaints that one diagnosis cannot hold, acupuncture’s whole-system approach often explains more than any single-tissue model. That is not a rejection of anatomy; it is a second lens, and some patients need both.
Needle fear: the honest version
Needle phobia stops more people from trying these treatments than any evidence concern, so the honest version:
- The needles used in both practices are hair-thin, nothing like injection needles
- Most patients rate insertion as 0 to 1 out of 10; the dry needling twitch is the notable moment, and it lasts about a second
- Phobic patients can start with fewer needles, shallower techniques, or acupuncture’s retained-needle calm, which many needle-nervous patients find deeply relaxing
- Saying “I am nervous about needles” at the start changes the plan; the clinician’s job includes pacing
The patients most surprised are usually the needle-phobic ones: the anticipated experience and the actual one live far apart.
Where dry needling fits inside physiotherapy
In our clinic, dry needling is a tool inside a plan, never the plan itself. The typical sequence:
- Assessment finds the drivers: the trigger points, the weakness, the load patterns
- Needling releases what is stuck, often in the same session as the first exercises
- The loading program rebuilds what has been guarding, so the trigger point does not return next month
- Follow-up needling treats new spots as the patterns unwind
The release without the rebuild is why some patients report “needling worked but it came back.” The trigger point is the symptom of a load pattern; the plan treats both halves.
The classic cases where needling earns its keep
- The deep gluteal pain that stretching never reaches: piriformis trigger points are a dry needling showcase
- The tension headache cluster: neck and shoulder girdle trigger points referring to the head
- The runner’s calves: chronic tightness that foam rolling manages but never resolves
- The post-injury guarding: muscles that locked down around an injury and never released
Where acupuncture fits in the modern clinic
Acupuncture in a multidisciplinary clinic serves three groups well:
- The chronic pain patient whose system is sensitized: the whole-body approach quiets the alarm
- The stressed patient whose pain and sleep feed each other: the sessions rebuild the off-switch
- The patient between physiotherapy phases: acupuncture maintains momentum during the quieter weeks
The style matters as much as the theory: the retained-needle session is rest the modern week rarely provides, and the rest itself is therapeutic. Patients often name the hour on the table as the calmest of their month.
Training and regulation: who is doing the needling
Ontario regulates both practices, and the credentials differ:
- Physiotherapists performing dry needling: trained within their regulated scope, typically through post-graduate certification building on their anatomy training
- Acupuncturists: registered with the College of Traditional Chinese Medicine Practitioners and Acupuncturists of Ontario after a full degree or diploma program
Both registrations are checkable, and both matter: the needle’s safety lives in the map behind it. Ask any clinic who holds the needle and what their training was; the good ones enjoy the question.
Where dry needling fits inside physiotherapy
At Tonic Physio, dry needling is a tool inside a plan, never the plan itself. The typical sequence:
- Assessment finds the drivers: the trigger points, the weakness, the load patterns
- Needling releases what is stuck, often in the same session as the first exercises
- The loading program rebuilds what has been guarding, so the trigger point does not return next month
- Follow-up needling treats new spots as the patterns unwind
The release without the rebuild is why some patients report “needling worked but it came back.” The trigger point is the symptom of a load pattern; the plan treats both halves.
The classic cases where needling earns its keep
- The deep gluteal pain that stretching never reaches: piriformis trigger points are a dry needling showcase
- The tension headache cluster: neck and shoulder girdle trigger points referring to the head
- The runner’s calves: chronic tightness that foam rolling manages but never resolves
- The post-injury guarding: muscles that locked down around an injury and never released
Where acupuncture fits in the modern clinic
Acupuncture in a multidisciplinary clinic serves three groups well:
- The chronic pain patient whose system is sensitized: the whole-body approach quiets the alarm
- The stressed patient whose pain and sleep feed each other: the sessions rebuild the off-switch
- The patient between physiotherapy phases: acupuncture maintains momentum during the quieter weeks
The style matters as much as the theory: the retained-needle session is rest the modern week rarely provides, and the rest itself is therapeutic. Patients often name the hour on the table as the calmest of their month.
Training and regulation: who is doing the needling
Ontario regulates both practices, and the credentials differ:
- Physiotherapists performing dry needling: trained within their regulated scope, typically through post-graduate certification building on their anatomy training
- Acupuncturists: registered with the College of Traditional Chinese Medicine Practitioners and Acupuncturists of Ontario after a full degree or diploma program
Both registrations are checkable, and both matter: the needle’s safety lives in the map behind it. Ask any clinic who holds the needle and what their training was; the good ones enjoy the question.
Answers to the questions patients ask most
Is dry needling the same as acupuncture?
Same needle, different practice. Dry needling targets muscle trigger points on a Western anatomical map; acupuncture treats through the traditional meridian system. The training paths, philosophies, and session structures differ completely.
Which one hurts more?
Dry needling produces the twitch, a brief intense cramp that surprises people. Acupuncture produces almost no insertion sensation and a retained-needle calm. During the session, dry needling is more eventful; the day after, both leave similar mild muscle soreness.
How many sessions will I need?
Dry needling: often 1 to 3 per region, integrated into a physiotherapy plan. Acupuncture: typically 4 to 8 weekly sessions for systemic patterns. Your assessment sets the expectation before the first needle.
Can I have both in the same week?
Yes, and many patients do: dry needling with the physiotherapist for the specific drivers, acupuncture later in the week for the system. The two styles complement rather than compete.
Does insurance cover them?
Most extended plans cover both when delivered by registered practitioners, often under separate benefit categories (physiotherapy for dry needling, acupuncture for acupuncture). Direct billing handles most major insurers; bring your card and the desk sorts the lanes.



